 21 0686 2040


Spinal Fracture

What is a spinal fracture?
The spine protects internal organs and the spinal cord while also allowing movement. It is extremely stable and requires significant force to sustain a spinal fracture. The spine consists of 24 vertebrae, along with the sacrum and a complex system of ligaments and muscles, forming a flexible structure that absorbs high-energy impacts before fracturing.
At what age do spinal fractures occur?
Most fractures occur in two age groups:
- Young individuals—caused by high-impact trauma (e.g., car accidents, diving into shallow water, falls from heights, extreme sports).
- Elderly individuals—due to osteoporosis, making them vulnerable because of reduced bone density.
Half of the patients with spinal fractures also have another injury in a different part of the body. In 20% of cases, multiple vertebral fractures occur. While the likelihood of spinal cord injury increases with higher trauma energy, the overall risk of neurological damage remains low. The most common spinal fractures occur in the lumbar spine or the thoracolumbar junction.
Apart from traumatic fractures, there are also pathological fractures caused by:
- Osteoporosis or osteomalacia (vitamin D deficiency)
- Primary or metastatic spinal cancer
- Spondylitis (bone inflammation)
In such cases, fractures may occur with little or no trauma.
What are the symptoms?
The main symptom is pain at the site of the fractured vertebra and surrounding spinal segments, along with restricted spinal mobility. If a nerve is compressed, pain may radiate down the leg or arm. If the spinal cord is compressed, motor or sensory impairments may occur, either temporarily or permanently.
How is a spinal fracture diagnosed?
Diagnosis involves a detailed medical history, where the doctor assesses the trauma mechanism, energy involved, and any conditions that can help determine the fracture type and severity even before imaging tests.
A thorough physical and neurological examination follows, evaluating the patient’s ability to walk, muscle strength, sensation, and reflexes in the limbs. This helps determine the extent of spinal cord damage and the need for immediate surgery.
Final diagnosis is confirmed through imaging tests:
- X-ray (now largely replaced by CT scans due to its limitations).
- CT scan (provides detailed analysis of bone structures, even in difficult areas like the cervicothoracic junction).
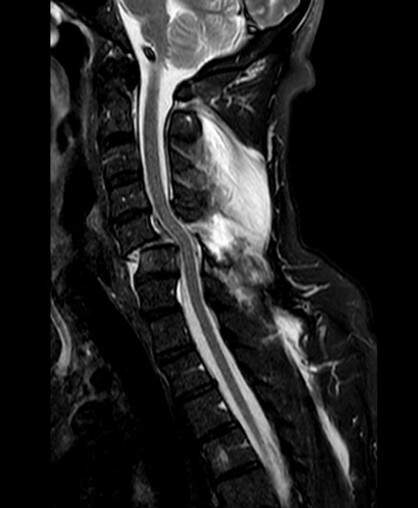
- MRI scan (essential for high-impact fractures to assess ligament damage and differentiate between old and new fractures in osteoporotic cases).
Fractures are classified as stable or unstable:
- Stable fractures: Soft tissues and ligaments are intact, and the spinal canal is not significantly compromised (85% of cases, treated non-surgically).
- Unstable fractures: The spine cannot support body weight in an upright position, often requiring surgical intervention.

Treatment Options
Treatment can be either conservative (non-surgical) or surgical.
Conservative Treatment
Most fractures are stable and do not require surgery. They are treated with:
- Spinal immobilization using a brace or collar (for cervical fractures) for 1.5 to 3 months.
- Pain relievers.
- Avoiding heavy lifting and excessive spinal bending.
- Once healed, rehabilitation with core strengthening and aerobic exercise.
Historically, strict bed rest was recommended, but it is now avoided, as even severe fractures can be managed with a brace, preventing complications associated with prolonged immobility.
Surgical Treatment
Surgery is required for:
- Fracture-dislocations.
- Neurological symptoms, especially if worsening.
- Multiple trauma patients.
- Patients who cannot tolerate a brace (e.g., obese individuals).
- Special cases (e.g., patients with ankylosing spondylitis).
The standard procedure is spinal fusion (spondylodesis), increasingly performed minimally invasively with small incisions and sometimes navigation systems. In severe cases where vertebrae are severely damaged or bone fragments compress nerves, anterior spinal access and bone fragment removal may be necessary.
For low-impact fractures (e.g., osteoporotic fractures) that remain painful despite treatment, kyphoplasty is highly effective. This minimally invasive procedure involves injecting bone cement into the fracture via a needle, stabilizing it instantly and relieving pain.
Regardless of treatment type, rehabilitation (including spinal muscle strengthening and general conditioning) is essential after 2-3 months for full recovery.

Frequently Asked Questions about Spinal Fractures
What is the difference between a traumatic and a pathological vertebral fracture?
Traumatic fractures result from strong forces (a fall, a car accident), while pathological fractures happen because the bones are weak due to conditions such as osteoporosis or tumors, and can occur even without an obvious injury.
Can I walk with a vertebral fracture?
All patients who have no nerve damage can and should walk after a fracture.
How serious is a spinal fracture?
In traumatic fractures, the severity depends on how serious the accident was. Osteoporotic fractures, however, completely disrupt patients’ lives and often have a poor outcome, just like hip fractures. That is why immediate mobilization (not bed rest) is essential.
When is surgery needed?
As a rule, when the fracture comes with nerve damage, or with pain that does not go away and leaves the patient bedridden and unable to function.
How long is the recovery, with or without surgery?
In stable fractures, immobilization in a brace or collar lasts 1.5 to 3 months, and after surgery a period of 2 to 3 months is usually enough for the fracture to heal. Physiotherapy follows. In every case, the goal is to get the patient moving. Full recovery is possible after intensive physiotherapy, whether or not surgery came first.
What should I watch out for in my daily life during recovery?
Avoid lifting weights and bending the spine, and follow the physiotherapy instructions. Recovery should be gradual and careful.
What exercises are done after a vertebral fracture?
Once the fracture has healed, the patient should start rehabilitation, mainly with core strengthening and aerobic exercise. After surgery too, once the fracture has healed, physiotherapy focuses on strengthening the spinal muscles and the patient’s general fitness. Until then, lifting weights and bending the spine are avoided.
How is a vertebral fracture from a fall treated?
About 85% of spinal fractures are stable and are treated without surgery, with immobilization in a brace or collar (if it is in the neck) for 1.5 to 3 months, painkillers and avoiding lifting and bending, while bed rest has no place. In elderly people with osteoporosis, a fracture can happen even with minimal force. If the pain from an osteoporotic fracture persists despite treatment, minimally invasive kyphoplasty is indicated.